What Hospitals Should Know About Managed Detection and Response Services

Date
Authors
Tony UV
Follow Us


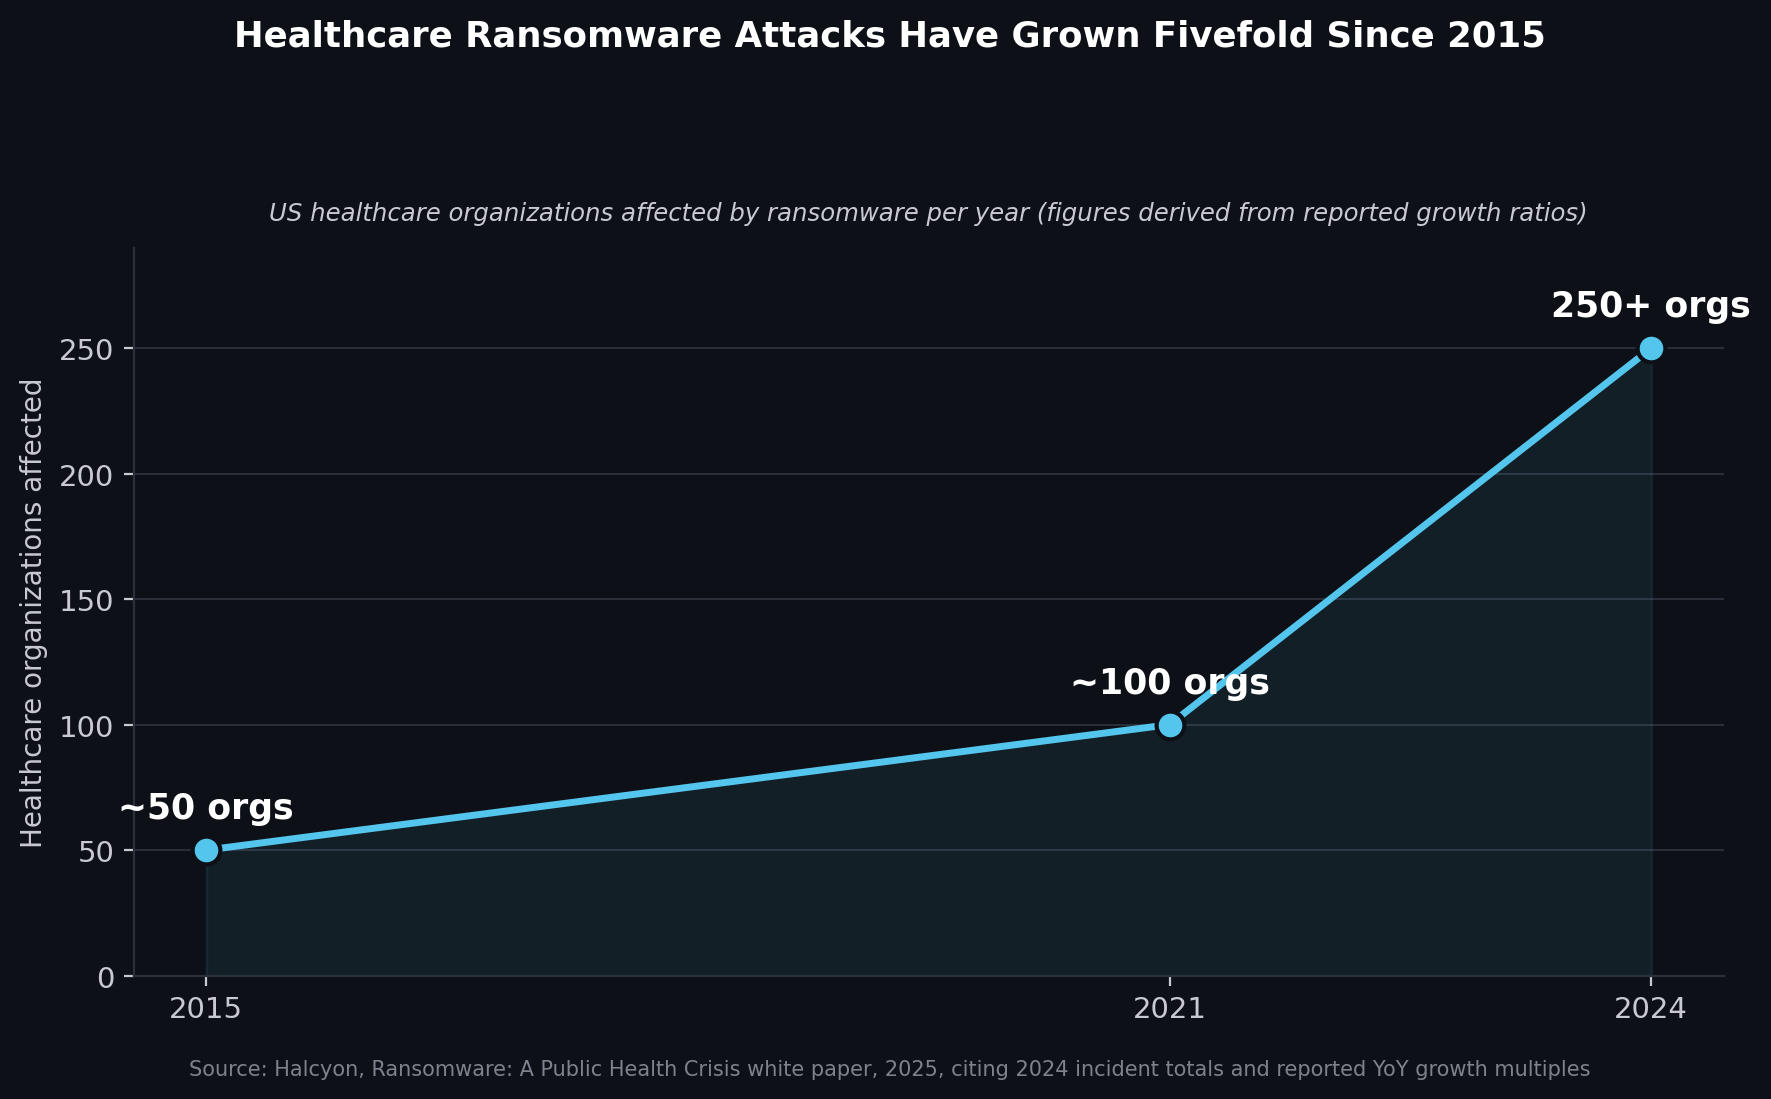
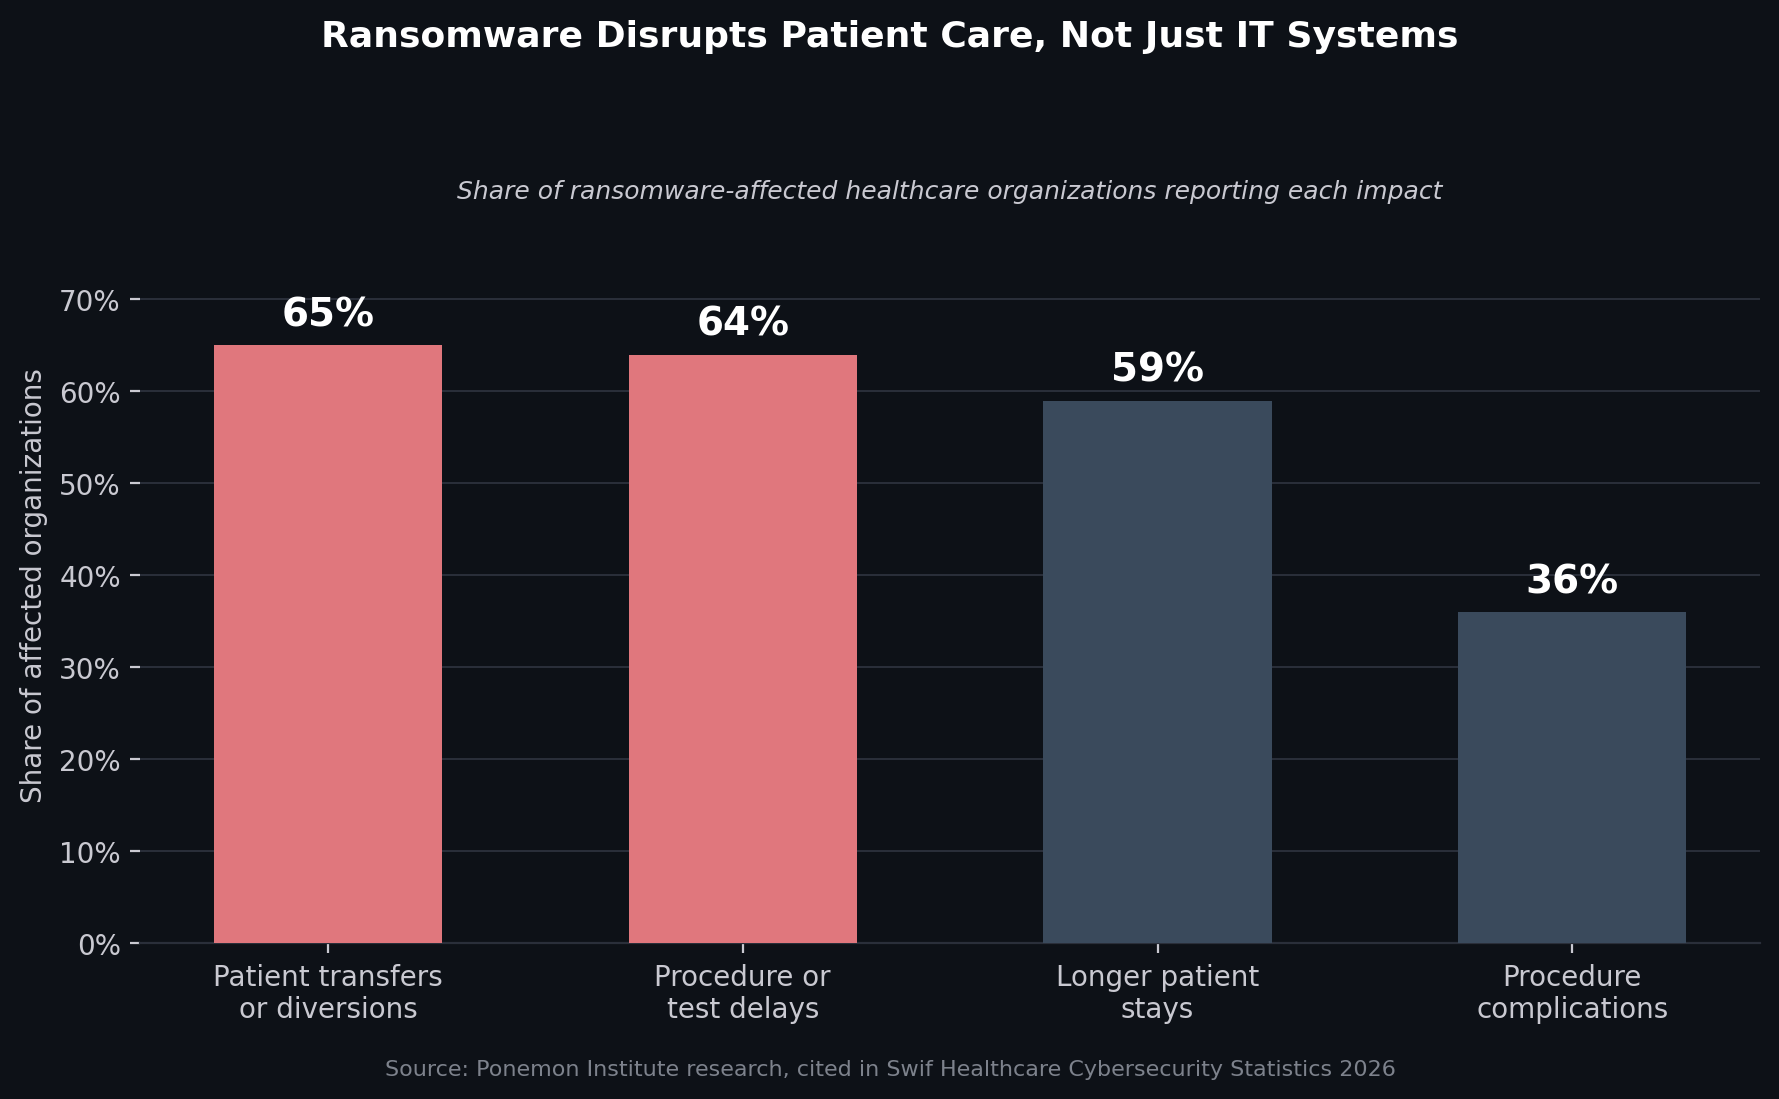
Most guidance on evaluating a managed detection and response provider is written for a generic enterprise buyer, and generic enterprise criteria miss the specific operational realities of a hospital environment. Managed detection and response services for hospitals need to account for things a typical corporate SOC engagement doesn’t: connected medical devices that can’t run standard agents, incident response that can’t simply take a clinical system offline, and reporting obligations under HIPAA that a general enterprise contract doesn’t address. The stakes are not abstract: healthcare organizations affected by ransomware have grown roughly fivefold since 2015, and Ponemon Institute research found that ransomware caused patient transfers or facility diversions at 65 percent of affected organizations and procedure or test delays at 64 percent. Below are the criteria that actually matter when evaluating an MDR provider for a hospital or health system specifically, not a generic enterprise checklist with “healthcare” inserted into the title.
1. 24×7 Coverage That Actually Means 24×7
Many MDR contracts describe “24×7 coverage” that, in practice, means after-hours alerts get forwarded to an on-call queue rather than actively triaged by a staffed analyst. For a hospital, where patient-facing systems operate continuously, and an attacker has no reason to wait for business hours, that distinction matters more than the marketing language suggests.
What a strong answer looks like: A provider that can describe exactly who is actively monitoring alerts at 3 a.m. on a Sunday, what their actual response time commitment is at that hour specifically, and whether escalation to a senior analyst happens automatically or requires someone junior to first recognize they’re out of their depth.
2. Detection Logic Tuned to Healthcare, Not Just Applied to It
A detection rule set built for a generic enterprise and pointed at a hospital network will catch generic enterprise threats. It won’t reliably catch the exfiltration patterns specific to large volumes of protected health information moving through clinical systems, or the specific behavior of ransomware strains that have targeted healthcare disproportionately.
What a strong answer looks like: A provider who can point to detection content specifically built or tuned for healthcare environments, not just a claim that their general rule set “works for healthcare too,” and who can describe how that tuning differs from what they’d deploy for a retail or manufacturing client.
3. Genuine Support for Connected Medical Devices
A significant share of hospital network devices, infusion pumps, imaging equipment, patient monitors, can’t run a standard endpoint agent at all. An MDR provider whose entire detection model assumes agent-based visibility has a structural blind spot across exactly the device category that carries the most direct patient safety risk if compromised.
What a strong answer looks like: A specific description of how the provider monitors and detects threats on agentless or agent-limited medical devices, rather than a general assurance that “we cover your whole environment” without addressing how.
4. Incident Response That Accounts for Clinical Uptime
A standard containment playbook often assumes a compromised system can be isolated or taken offline immediately. In a hospital, that assumption can directly conflict with patient care happening on or through that system in real time, and the data on what actually happens during a hospital ransomware attack makes this concrete rather than theoretical. Ponemon Institute research found that ransomware attacks caused longer patient stays at 59 percent of affected healthcare organizations and complications from medical procedures at 36 percent. A peer-reviewed economics study examining hospital ransomware attacks found in-hospital mortality for patients already admitted at an attacked hospital increased by 1.28 to 1.87 percentage points during the attack window.
What a strong answer looks like: A provider who asks about clinical uptime constraints during scoping, before an incident happens, and can describe how their containment approach adapts when a standard response would disrupt active patient care.
5. HIPAA-Aligned Reporting and Documentation
A hospital’s compliance team needs incident documentation that maps to HIPAA breach notification requirements, not a generic security incident report that has to be manually translated into HIPAA-relevant language after the fact, under deadline pressure, during an actual incident.
What a strong answer looks like: Sample reporting or documentation templates that already reflect HIPAA-relevant categories and language, reviewed before signing, not promised as a future customization.
6. A Real Analyst-to-Client Ratio, Not Just a Company Size
Company size is a weak proxy for the attention a specific hospital account will actually receive. SOC-wide research consistently documents alert volumes and analyst burnout at levels that would compromise service quality regardless of whether the provider is large or small, if account load isn’t managed deliberately.
What a strong answer looks like: A direct answer to how many client accounts a given analyst or account team is actually responsible for, and how the provider prevents that number from growing to the point where a hospital’s specific environment becomes unfamiliar to the person reviewing its alerts.
7. Integration With Existing Hospital IT and Security Tools
Hospitals frequently operate a mix of legacy clinical systems, specialized medical device management platforms, and standard IT infrastructure. An MDR provider whose platform only integrates cleanly with modern, standard enterprise tooling may leave the legacy and clinical-specific portions of the environment outside effective monitoring.
What a strong answer looks like: A specific, honest answer about which of the hospital’s actual existing systems the provider has integrated with before, versus which would require new integration work, scoped and estimated before the contract is signed.
8. Transparent, Scalable Pricing
Hospital IT budgets are frequently constrained relative to the scope of what needs protecting, and an MDR engagement that starts affordable and scales unpredictably as device count or data volume grows can create a difficult renewal conversation a year in.
What a strong answer looks like: A pricing model with clear cost drivers disclosed upfront, tied to metrics the hospital can actually forecast, device count, data volume, or user count, rather than opaque tiering that changes significantly at renewal.
Weighing These Criteria Together
No single criterion above is disqualifying on its own, but the pattern across a prospective provider’s answers is informative. A provider who can speak specifically to clinical uptime, medical device visibility, and HIPAA-aligned reporting, without prompting, is describing a program built with hospital operations in mind. A provider who answers every question with a version of “our standard offering covers that” is describing a generic enterprise product with a healthcare label attached. Given the documented scale of ransomware’s operational and patient-safety impact, that distinction is worth the extra diligence during evaluation, not something to take on faith from a sales conversation.